Echo Parasternal Short Axis View Diagram: Proper Routing 2026
The parasternal short axis view diagram illustrates cross-sectional cardiac structure by positioning the ultrasound transducer in the 3rd or 4th left intercostal space, rotated 90 degrees clockwise from the long axis view toward the left shoulder. It maps key levels including aortic valve, mitral valve, and papillary muscle system configurations.
📌 Key Takeaways
- Position transducer at the 3rd to 4th left intercostal space rotated 90 degrees clockwise toward the left shoulder
- Identifies five primary levels: aortic valve, mitral valve, papillary muscles, apex, and right ventricular outflow tract
- Standard orientation displays the right ventricle superiorly and the left ventricle as a circular inferior structure
- Acoustic shadowing and rib interference represent the most common image degradation artifact points
- Clinical diagnostic interpretation requires formal sonographer training and medical board verification
The parasternal short axis view diagram serves as a critical technical schematic for diagnostic imaging specialists, biomedical equipment technicians, and clinical systems engineers calibrating high-frequency ultrasound hardware. Capturing perpendicular cross-sectional planes of the cardiac structures along the short axis, this diagnostic projection requires precise transducer beam steering, proper Time-Gain Compensation (TGC) adjustment, and accurate multi-element phased array signal processing. Understanding this structural schematic allows technical personnel to evaluate system spatial resolution across varying focal depths, calibrate beamformer delay lines, verify transducer acoustic output, and isolate signal artifacts caused by hardware misconfiguration or acoustic window impedance variations.


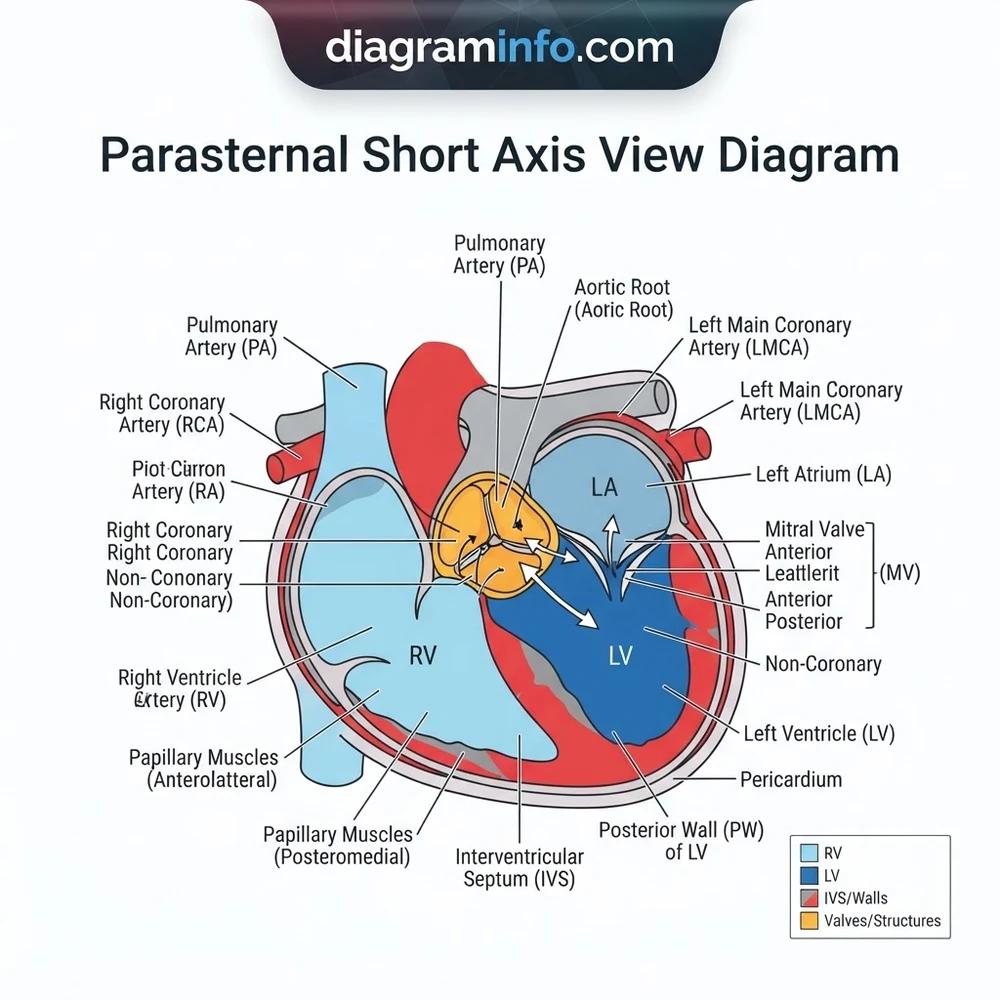
Parasternal Short Axis View Diagram Component Breakdown and Structure


Evaluating a complete parasternal short axis view diagram requires analyzing four discrete cross-sectional slicing planes orthogonal to the long axis of the left ventricle. Each plane isolates specific anatomical target structures, acoustic reflectors, and structural geometries required for hardware signal calibration and clinical assessment.
Aortic Valve Level Component Layout
Located at the most basal slice of the heart, the aortic valve level schematic illustrates a characteristic “Mercedes-Benz” sign formed by the three aortic valve cusps: coronary (right and left) and non-coronary. Surrounding this central circular structure are the right ventricular outflow tract (RVOT) anterolaterally, the pulmonary valve and main pulmonary artery laterally, the right atrium inferiorly, and the interatrial septum. Biomedical technicians utilize this specific plane to verify lateral resolution and side-lobe suppression, as the thin leaflets demand crisp boundary definition without reverberation clutter.
Mitral Valve Level Signal Structure



Slicing slightly more apically, the mitral valve level diagram displays the oval cross-section of the left ventricle containing the anterior and posterior mitral valve leaflets. In a healthy system layout, the leaflets open into a distinct “fish-mouth” configuration during diastole. The right ventricle appears as a crescent-shaped chamber wrapped around the anterior-septal boundary of the left ventricle. This level is essential for testing frame-rate responsiveness and dynamic range settings, ensuring high temporal resolution along the rapidly moving leaflet edges.
Papillary Muscle Level Structural Blueprint
Positioned midway down the left ventricular cavity, the papillary muscle plane reveals two distinct muscular prominences: the anterolateral papillary muscle (located at approximately the 3 o’clock to 4 o’clock position) and the posteromedial papillary muscle (located at approximately the 7 o’clock to 8 o’clock position). The left ventricle exhibits a symmetrical, thick-walled “donut” ring geometry. According to OEM technical specifications, this section provides the benchmark for wall motion analysis, echo intensity calibration, and acoustic attenuation correction across deep tissue depth settings.
Apical Level System Configuration


The most distal slice represents the left ventricular apex, showing a small, circular cavity without papillary muscle structure. This view verifies beam penetration, focal zone accuracy, and signal-to-noise ratios (SNR) at maximum diagnostic depths (15 cm to 22 cm).


When testing phased array transducers, the parasternal short axis view diagram requires an acoustic transmission frequency between 2.0 MHz and 4.0 MHz for adult hardware configurations, and 5.0 MHz to 8.0 MHz for pediatric diagnostic systems. Ensure transducer element impedance remains within nominal range (50 ohms nominal) before adjusting beamformer focus zones.
How to Read the Parasternal Short Axis View Diagram Configuration


Reading and interpreting the parasternal short axis view diagram configuration demands a systematic approach to coordinate axes, orientation markers, and acoustic acoustic reflection levels.
Step 1: Orienting Transducer Indexing and Beam Trajectory
Begin by identifying the orientation marker on the schematic. On a standard parasternal short axis view diagram layout, the transducer orientation marker corresponds to the right side of the displayed image (conventionally positioned on the right side of the screen at the 1 o’clock to 2 o’clock position relative to the patient’s right shoulder). The top of the diagram represents the near-field (chest wall interface and anterior right ventricular wall), while the bottom represents the far-field (posterior left ventricular wall and pericardium).
Step 2: Evaluating Wall Symmetry and Chamber Geometry


Examine the circular shape of the left ventricle at the papillary muscle level. A properly calibrated imaging system showing a true short-axis cut will display a perfectly symmetrical, circular left ventricular lumen. If the cavity appears elliptical, the ultrasound beam axis is tilted obliquely relative to the long axis of the heart, introducing foreshortening artifacts that skew wall thickness measurement values.


Step 3: Checking Time-Gain Compensation and Signal Uniformity
Trace the acoustic reflectivity from the near-field anterior wall down to the deep posterior wall structures. Verify that tissue echogenicity remains uniform throughout the myocardium. Adjust the Time-Gain Compensation (TGC) slide controls on your diagnostic console to balance attenuation losses, ensuring that signal strength does not drop off excessively in the deep field (greater than 10 cm depth). Reference our detailed ultrasound transducer phased array maintenance guide for hardware troubleshooting protocols if gain equalization fails.
Do not perform digital gain boosts above +18 dB on uncalibrated systems without checking mechanical index (MI) limits. Over-amplifying acoustic noise can mask micro-calcifications or simulate intraluminal thrombi within the left ventricular apex.
System Blueprint and Acoustic Window Measurement Specs


To ensure hardware diagnostic accuracy, system performance parameters must conform strictly to manufacturer operational tolerances. The table below outlines technical acquisition standards, frequency bounds, and structural tolerances across the four parasternal short axis diagram levels based on standard OEM diagnostic benchmarks.
| Plane Level | Target Focal Depth (cm) | Transducer Freq Range | Nominal Dynamic Range | Structural Geometry Standard |
|---|---|---|---|---|
| Aortic Valve Level | 4.0 – 8.0 cm | 2.5 MHz – 5.0 MHz | 60 dB – 75 dB | Tri-radiate symmetric cusp closure (“Y” pattern) |
| Mitral Valve Level | 6.0 – 10.0 cm | 2.0 MHz – 4.0 MHz | 55 dB – 70 dB | Bicuspid leaflet motion (“fish-mouth” opening) |
| Papillary Muscle Level | 8.0 – 14.0 cm | 2.0 MHz – 3.5 MHz | 50 dB – 65 dB | Concentric LV ring with 4 & 8 o’clock muscle heads |
| Apical Level | 12.0 – 18.0 cm | 1.8 MHz – 3.0 MHz | 45 dB – 60 dB | Small circular myocardial ring without luminal muscles |
Mechanical Index (MI) should be maintained between 0.9 and 1.1 for standard B-mode imaging in short axis views. Thermal Index for Soft Tissue (TIS) must not exceed 1.0 during extended calibration runs exceeding 15 minutes.
Hardware technicians must verify signal phase coherence across all 64 to 128 active crystal channels in the phased array assembly. System signal-to-noise specs dictate that axial resolution must be less than or equal to 1.0 mm, while lateral resolution should remain under 1.5 mm at the mid-field focus zone (8.0 cm depth). For full electrical routing and signal chain configurations, refer to our beamformer circuit calibration specifications.
Troubleshooting Common Parasternal Short Axis View Diagram Signal Artifacts
When analyzing a parasternal short axis view diagram on diagnostic consoles, hardware faults, acoustic interference, or improper system configuration can produce severe image degradation. Understanding the root cause of these schematic distortions is essential for rapid diagnosis and equipment repair.
1. Vertical Acoustic Dropout and Element Failure
Symptom: Distinct black vertical line or acoustic shadow extending straight down through the sector field, cutting across the left ventricular cross-section.
Cause: A dead or damaged piezoelectric crystal element within the phased array transducer assembly, broken micro-coaxial wiring within the cable harness, or a blown channel transmitter channel on the system beamformer PCB.
Diagnostic Fix: Run an automated element micro-probe test on the system console. Check transducer connector pin continuity and inspect micro-coax solder joints. If individual element impedance exceeds 150 ohms, replace the transducer probe.
2. Severe Reverberation Noise in the Near Field
Symptom: Spurious parallel echo bands appearing inside the anterior right ventricular wall and near-field left ventricular lumen, obscuring structural boundaries on the diagram layout.
Cause: Excessive near-field overall gain settings, damaged acoustic matching layer on the transducer face, or poor acoustic gel coupling at the patient contact point.
Diagnostic Fix: Lower the top two Time-Gain Compensation (TGC) sliders (-3 dB to -6 dB). Inspect the probe lens surface for delamination, chips, or air pockets under the silicone acoustic window.


3. Elliptical Cavity Distortion (Foreshortening)
Symptom: The left ventricle appears as an elongated oval or egg shape at the papillary muscle plane rather than a true circle, leading to false wall thickness and ejection fraction values.
Cause: Transducer array positioning is off-axis, slicing obliquely across the interventricular septum rather than perpendicular to the cardiac long axis.
Diagnostic Fix: Rotate the physical transducer 90 degrees clockwise relative to the long-axis plane, slide the probe higher or lower by one intercostal space (typically 3rd or 4th intercostal space), and ensure the acoustic beam strikes the heart walls at a true 90-degree angle.
4. Attenuation Loss and Far-Field Signal Dropout
Symptom: Complete loss of structural detail at the posterior left ventricular wall and pericardial border on deep apical views.
Cause: Frequency selection set too high for deep penetration, insufficient far-field TGC gain boost, or defective system High-Voltage (HV) power supply rails feeding the beamformer.
Diagnostic Fix: Switch the system pulse frequency to a lower setting (e.g., from 4.0 MHz down to 2.0 MHz). Increase the bottom three TGC sliders. Check the system +100V/-100V HV rail supply voltages under active transmit load conditions using a digital multimeter. Adjust Doppler signal processing optimization manual controls if spectral noise persists.
Parasternal Short Axis View Diagram Technical System FAQ
What transducer frequency is optimal for capturing a clear parasternal short axis view diagram?
For adult diagnostic systems, an operational center frequency between 2.0 MHz and 3.5 MHz provides the optimal balance of acoustic penetration and spatial resolution through thoracic bone and tissue interfaces. For pediatric or thin-window subjects, higher frequencies between 5.0 MHz and 8.0 MHz deliver superior axial resolution across smaller cross-sectional fields.
How do you identify a failing piezoelectric element on a parasternal short axis view diagram?
A failing or dead piezoelectric crystal element manifests as a permanent dark vertical strip (acoustic shadow dropout line) running vertically down through the sector cone. This dropout remains stationary regardless of probe position or tissue movement. Element mapping diagnostic software running on the console can confirm channel impedance spikes or zero-voltage returns.
What causes cross-sectional asymmetry in the mitral valve level layout?
Asymmetry at the mitral valve level is primarily caused by improper beam steering or an oblique cutting plane (foreshortening). If the ultrasound array is tilted away from the true short-axis plane, one mitral leaflet will appear disproportionately larger or thicker than the other. Re-aligning the transducer perpendicular to the interventricular septum restores correct dual-leaflet “fish-mouth” symmetry.
How does Time-Gain Compensation affect signal resolution in deep papillary structures?
Time-Gain Compensation (TGC) amplifies incoming RF echo signals exponentially over time to offset depth-dependent acoustic attenuation (roughly 0.5 dB to 0.7 dB per centimeter per MHz in human soft tissue). Proper far-field TGC adjustment boosts deep papillary muscle reflection signals back into the linear dynamic range of the system receiver without over-saturating near-field structures.
Why is the 2 o’clock orientation marker position standard for this view?
Positioning the transducer index marker toward the patient’s right shoulder (2 o’clock position) rotates the acoustic scanning plane 90 degrees clockwise relative to the parasternal long axis view (which points to the right hip at 10 o’clock). This standard alignment ensures that the right ventricle is displayed anteriorly on the left side of the screen, adhering to standardized clinical imaging orientation conventions.
Step-by-Step Guide to Understanding the Parasternal Short Axis View Diagram
Identify – Locate the parasternal long axis view baseline before rotating transducer 90 degrees clockwise
Locate – Position the index marker toward the patient’s left shoulder between the 3rd and 4th intercostal spaces
Reference – Consult the diagram layout to confirm circular geometry of the left ventricle without oblique distortion
Connect/Route – Tilt the transducer superiorly to scan the aortic level or inferiorly toward the papillary muscle system
Verify – Ensure the right ventricle appears anterior and crescentic relative to the central left ventricular circle
Troubleshoot – Adjust transducer tilt and angle if rib shadows obscure the lateral or anterior myocardial wall segments